



Mechanism of Action vs Efficacy: What the Evidence Shows

TL;DR · The short version
Mechanism of action describes how an effect occurs. Efficacy describes a defined response or outcome in a specified setting. Potency concerns the concentration needed for a response. A stronger signal or lower EC50 does not establish a better clinical result.
Receptor activation answers a receptor question. Whether a defined outcome improves is another question requiring another measurement. That distinction is easy to lose when both appear under the same headline.
Mechanism of action vs efficacy becomes clearer when each measurement has a name. Potency, maximum assay response and a clinical outcome concern different properties. We’ll separate them before comparing claims.
Mechanism, potency and efficacy answer different questions
TL;DR: Mechanism, potency, pharmacological efficacy and clinical efficacy describe different properties.
| Term | Question to ask |
|---|---|
| Mechanism of action (MoA) | Through which interactions or processes does the effect occur? |
| Potency | What concentration or dose produces a specified response in this system? |
| Pharmacological efficacy | What maximal response can the agonist produce in the measured system? |
| Clinical efficacy | Does the intervention improve the defined outcome in the studied population under the trial conditions? |
The National Cancer Institute defines mechanism of action in terms of how an agent produces an effect. That explanation is distinct from measuring how large the effect is or showing that a particular clinical outcome improves.
What a concentration–response curve tells you
TL;DR: EC50 and Emax describe a concentration–response relationship in a specified assay, not overall usefulness or safety.
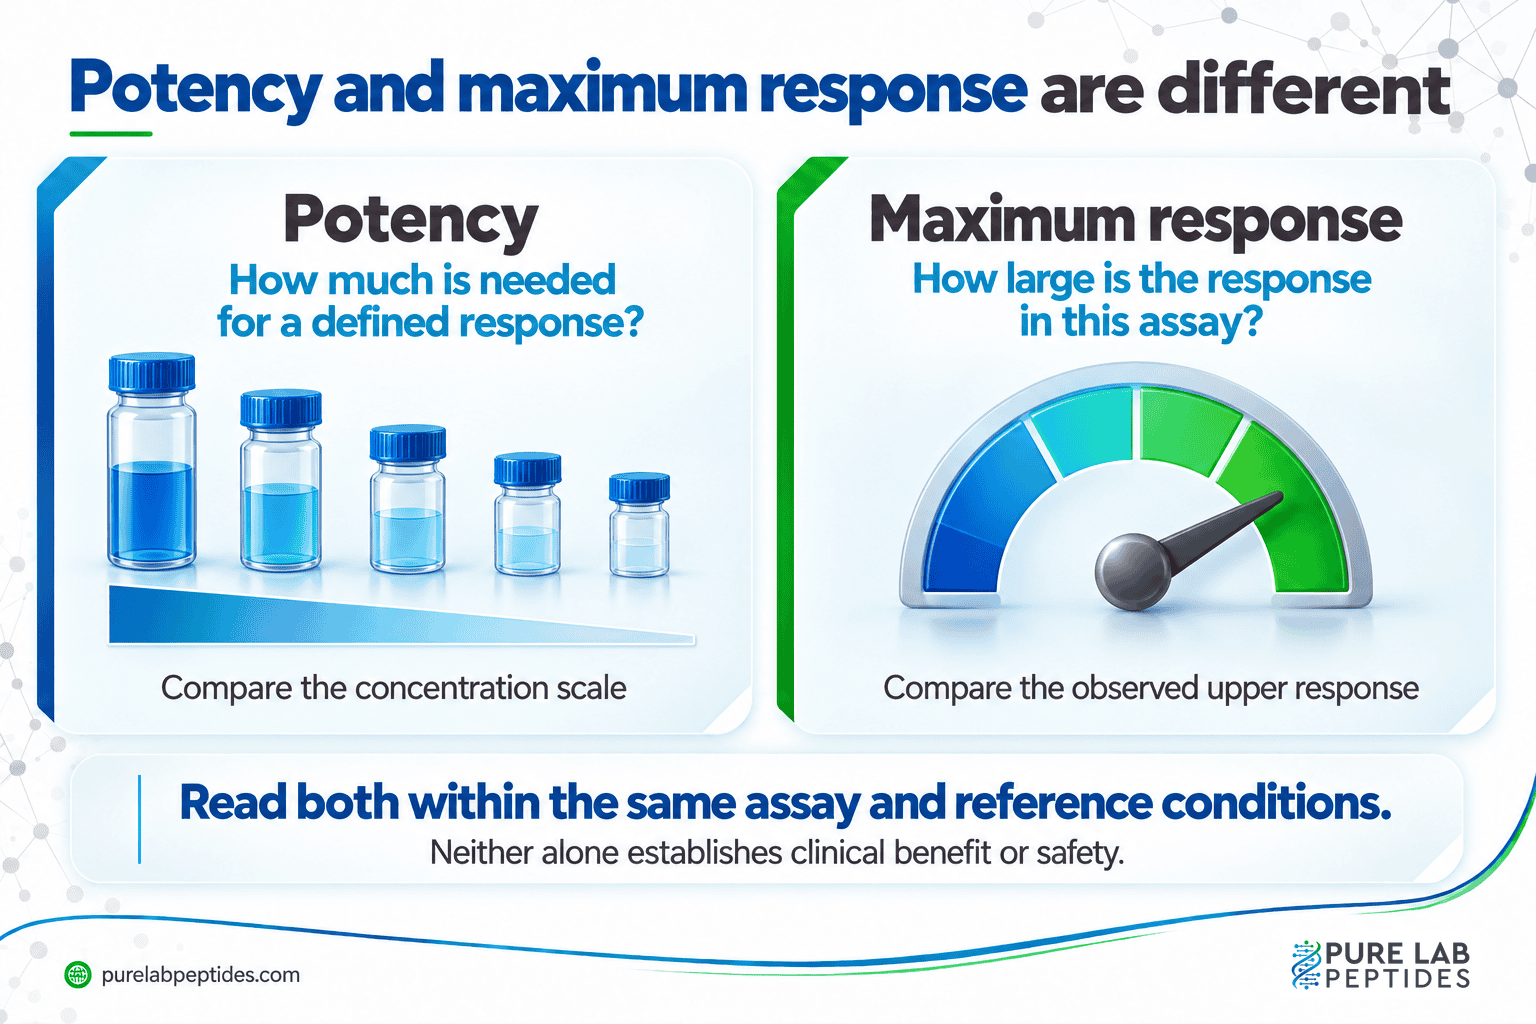
In a graded assay, EC50 denotes the concentration producing half of the compound’s maximal measured response. Emax describes the maximum response. These parameters help compare potency and efficacy when the endpoint and experimental conditions are comparable. Tulane’s pharmacology teaching resource explains this distinction.
In a hypothetical assay, two compounds reach the same Emax but one reaches half its maximum at a lower concentration. It is more potent in that assay, not higher in maximum response. The curve still leaves clinical outcomes and safety unanswered.
The Canadian Society of Pharmacology and Therapeutics describes full and partial agonists by their maximal responses. A partial agonist can bind receptors yet produce a lower response than a full agonist in the same system. Always specify the assay: receptor expression and the measured pathway can affect the observed comparison.
Follow the chain of evidence
TL;DR: Binding, signaling and downstream behavior each need evidence; one does not establish the whole chain.
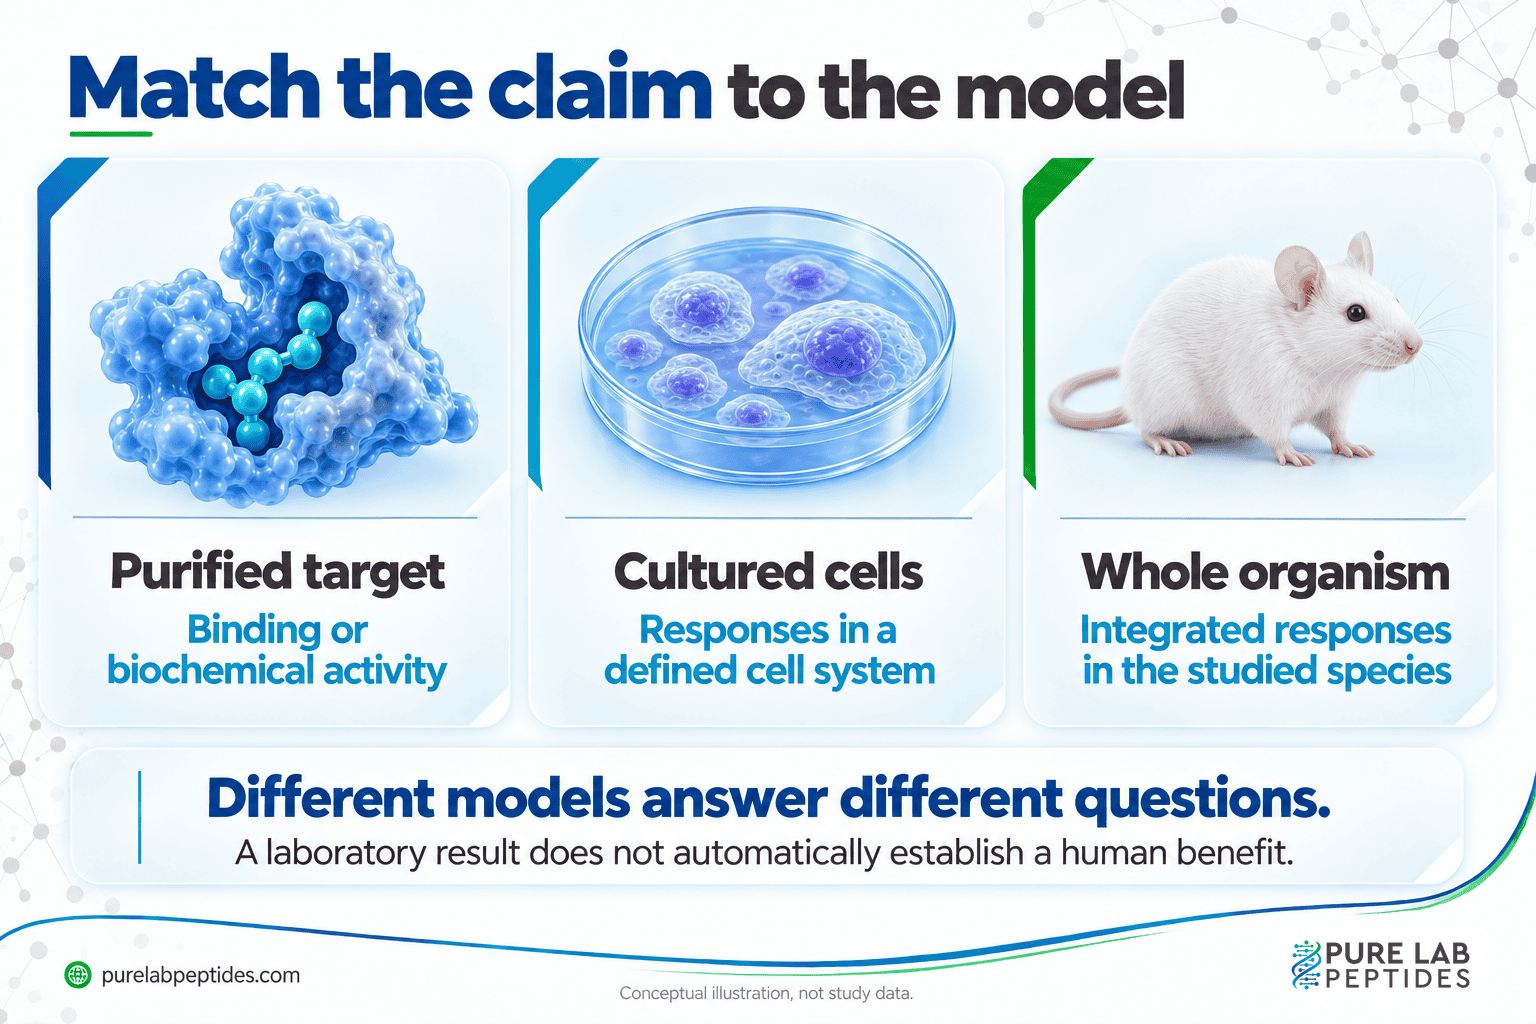
Binding, a downstream signal and changed cell behavior may form a proposed chain. Each link needs evidence. Measuring the first doesn’t establish the rest, and a downstream response alone doesn’t identify its cause.
| Reported observation | Appropriate interpretation |
|---|---|
| Interaction with a purified target | Evidence about that interaction under the assay conditions |
| Changed signaling in a cell system | A response in that system; causation may require additional experiments |
| Changed behavior in a model organism | An outcome in the stated model, not automatic human efficacy |
| High analytical purity | A material-characterization result, not a biological mechanism |
Keep the study’s model in the sentence
TL;DR: Include the tested model and endpoint when describing a result.
A BPC-157 experiment in rat tendon fibroblasts investigated growth-hormone-receptor expression and cell responses. Describing those observations is different from saying a product repairs human tendons. The latter changes both the endpoint and the biological setting.
A finding for an analogue, mixture or formulation needs a justified comparison before transfer to another material. A shared pathway or family name doesn’t establish equivalence.
What makes a mechanistic explanation stronger?
TL;DR: Controls, targeted interventions and independent measurements help distinguish explanations.
Look behind a pathway diagram’s arrows. Which controls, independent measurements and target-directed interventions tested the explanation? Replication and uncertainty then help you judge how well those links are supported.
The NIH preclinical reporting principles emphasize transparent design, sample size, analysis and replication. These details help a reader judge whether an explanation is well supported.
Clinical efficacy requires an outcome and a comparison
TL;DR: A clinical efficacy claim needs a defined population, comparison and outcome.
In a clinical paper, identify the participants, comparison and endpoint. Did a biomarker change, or did people feel or function differently? Report the actual measurement rather than treating these as the same outcome.
Consumer claims add another inference
TL;DR: A consumer outcome claim adds an inference beyond the laboratory measurement.
A statement about a personal health outcome goes beyond a laboratory observation. The FTC health-products guidance considers the scientific support and overall impression of express and implied claims. Adding “may” or placing a research disclaimer elsewhere does not automatically make an unsupported outcome claim accurate.
For a research material, describe its identity, experimental system, endpoint and limits. Those details retain the interesting science without promising that the supplied product produces an early study’s finding.
The guide to reading peptide research papers shows how to keep the model, controls and result together in a usable note.